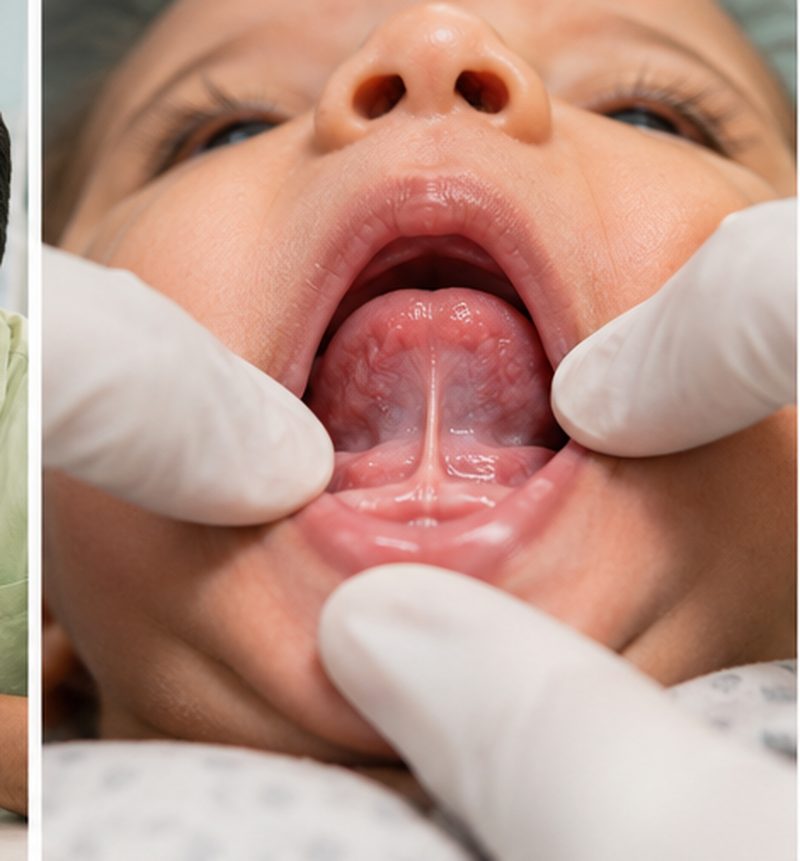
A frenulum is a small fold of tissue that anchors a more mobile part of the mouth. When it is unusually short or tight — called a "tie" — it restricts movement and function. LASER frenectomy releases this tissue in under 15 minutes, with no stitches, minimal discomfort, and immediate results.
Tongue Tie (Ankyloglossia)
Tongue tie affects around 4 to 10% of infants. The tight frenulum connecting the underside of the tongue to the floor of the mouth restricts how far the tongue can lift, extend, or cup — all movements needed for feeding, speech, and resting posture.
Signs in Infants
- Difficulty latching — the baby cannot cup the nipple effectively, leading to a shallow, painful latch.
- Clicking during feeds — the baby breaks the seal repeatedly, swallowing air.
- Poor milk transfer — slow weight gain despite long, frequent feeds.
- Maternal symptoms — nipple pain, mastitis, and blocked ducts are often the first sign of a tongue tie in the baby.
Signs in Children and Teens
- Speech difficulties — particularly "t," "d," "n," "l," "r," and "s" sounds that require tongue elevation.
- Cannot lick the upper lip or touch the roof of the mouth — a quick functional screening test.
- Open mouth posture — the tongue cannot rest on the palate, contributing to mouth breathing and narrow jaw development.
- Gap between lower front teeth — from constant tongue pressure at rest.
Lip Tie
A tight upper labial frenulum (connecting the upper lip to the gum between the front teeth) restricts the lip's ability to flange outward. Lip tie frequently accompanies tongue tie and is released in the same session when both are present.
- Newborns — the upper lip cannot flange properly during breastfeeding; the baby slides off the nipple and feeding is inefficient.
- School-age children — a persistent gap between the upper front teeth (midline diastema) that may not close with orthodontics alone without prior frenectomy.
- Orthodontic context — lip tie is a common cause of diastema relapse after brace treatment. Release is often recommended before or alongside orthodontics.
LASER vs Conventional Frenectomy
Conventional scissor or scalpel frenectomy requires stitches, causes more post-operative swelling, and takes 10 to 14 days to heal. LASER cuts and cauterises simultaneously — no stitches, less swelling, and most children heal in 5 to 7 days. Infants can breastfeed immediately after the procedure.
- Minimal bleeding — the LASER seals blood vessels as it cuts. The surgical field is clear throughout.
- No stitches — the wound heals cleanly without sutures.
- Less pain — the LASER is bactericidal and causes a smaller inflammatory response than a scalpel.
- Faster healing — 5 to 7 days versus 10 to 14 days with scissors.
- Immediate breastfeeding — infants go straight to the breast after the procedure. We follow a lactation-consultant-friendly protocol.
LASER-Assisted Root Canal
LASER energy sterilises the root canal more effectively than conventional instruments alone, reducing bacterial load by up to 99.7% before obturation. It is used as an adjunct alongside standard endodontic instruments — not as a replacement — and results in significantly less post-operative discomfort for children. Available for both baby tooth pulpectomy and permanent tooth root canal treatment at Dr. Mittal's clinics.
The Procedure — Step by Step
- Topical numbing gel — applied to the area for 2 minutes. Infants typically receive topical only; older children receive a small local anaesthetic injection.
- LASER release — 2 to 3 minutes. The tongue or lip frenulum is released precisely under the LASER. No scissors, no bleeding, no stitches.
- Immediate movement assessment — we check tongue elevation and lip flanging immediately after the release.
- For breastfed infants — the baby goes to the breast immediately. We observe the latch quality and confirm improvement before you leave.
- Stretching exercises demonstrated — we show you exactly how to perform the post-operative stretches and provide written instructions with photographs. These are the most important part of recovery.
The most common complication of frenectomy is reattachment — the body trying to heal the wound by reconnecting the tissue. Performing the demonstrated stretching exercises 4 to 5 times daily for 3 to 4 weeks dramatically reduces this risk. LASER frenectomy has a lower reattachment rate than conventional techniques, but the exercises are still essential.
Frequently Asked Questions
Related treatments: